influenza vs b strain comparison and global health dynamics

Published

Table of Contents

Influenza B strains present a distinct yet often underemphasized challenge in global virology, contrasting sharply with the more volatile influenza A subtypes. While influenza A dominates headlines due to its pandemic potential, influenza B’s stealthier evolution—marked by lower mutation rates and persistent lineage stability—demands rigorous examination of its epidemiological footprint, structural intricacies, and clinical nuances. This analysis dissects the historical trajectory of B-strain outbreaks, from localized epidemics to their disproportionate impact on vulnerable populations, while addressing diagnostic ambiguities and vaccine development hurdles that complicate public health responses. By synthesizing phylogenetic data, virological distinctions, and immunological responses, the discussion underscores why influenza B cannot be overlooked in seasonal preparedness strategies.

The interplay between influenza B’s genetic stability and its adaptive mechanisms—such as antigen drift in hemagglutinin proteins—shapes its transmission patterns and vaccine efficacy, often resulting in mismatched seasons with measurable consequences. Structural disparities, including the absence of neuraminidase in B strains, alter antiviral susceptibility and diagnostic reliability, necessitating advanced molecular techniques for accurate subtyping. Clinically, influenza B’s atypical presentations in pediatric and geriatric cohorts, coupled with its heightened severity in immunocompromised individuals, reveal a strain that punches above its weight in morbidity metrics. This exploration bridges epidemiological trends with virological innovation, offering a comprehensive framework for understanding why influenza B remains a critical yet frequently underestimated player in influenza surveillance and control.
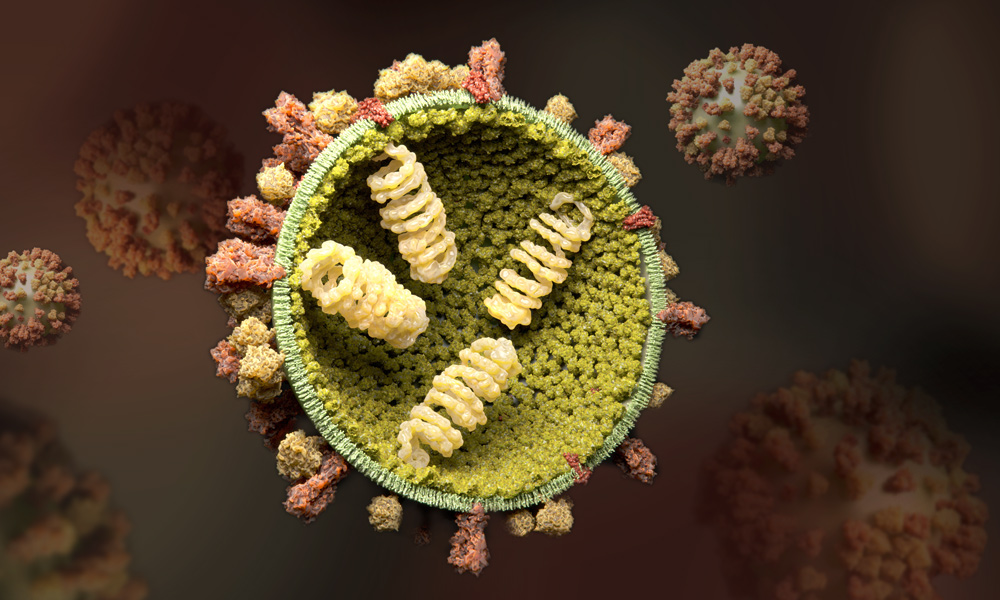
influenza vs b

Epidemiological and Historical Context of Influenza B-Strain Variations

Influenza B viruses, though less frequently discussed than their influenza A counterparts, play a critical yet distinct role in seasonal epidemics and global health dynamics. Unlike influenza A, which encompasses multiple subtypes (e.g., H1N1, H3N2) capable of interspecies transmission and pandemic potential, influenza B is restricted to humans and seals, exhibiting lower genetic diversity and a more stable antigenic evolution. This stability, however, does not diminish its public health significance, as B strains contribute to a substantial proportion of seasonal influenza cases, particularly in children and younger populations. The historical emergence of B lineages—B/Victoria and B/Yamagata—has shaped vaccine composition and highlighted the need for targeted surveillance to mitigate mismatches between circulating strains and vaccine formulations.

The phylogenetic divergence of influenza B into two distinct lineages in the 1980s marked a pivotal shift in its epidemiological behavior. While influenza A’s antigenic drift and shift are driven by high mutation rates and reassortment, influenza B’s evolution is characterized by slower genetic changes, primarily within the hemagglutinin (HA) protein. This slower drift allows for longer periods of vaccine effectiveness but also necessitates precise strain selection to avoid mismatches, which can reduce vaccine efficacy to as low as 10–30% in poorly matched seasons. Below, the historical context, lineage-specific trends, and vaccine performance are examined through a structured analysis of key events, genetic stability, and phylogenetic patterns.

Historical Emergence and Evolution of Influenza B Lineages

Influenza B viruses were first isolated in the 1940s, with the prototype B/Lee/1940 strain identified in the United States. For decades, a single lineage dominated global circulation until the mid-1980s, when a genetic divergence resulted in the emergence of two distinct clades: B/Victoria/2/1987 and B/Yamagata/16/1988. This bifurcation was confirmed through phylogenetic studies of the HA gene, revealing a clear separation between the two lineages, which have since coexisted in seasonal circulation.

The B/Victoria lineage exhibited early dominance in the 1990s, with notable outbreaks in 1993–1994 and 1997–1998, where it accounted for up to 70% of influenza B cases in some regions. Conversely, the B/Yamagata lineage gained prominence in the early 2000s, particularly during the 2002–2003 season, when it surpassed Victoria in prevalence. Since then, these lineages have alternated in dominance, with no single lineage consistently outperforming the other. The coexistence of both lineages since the 1990s has necessitated quadrivalent vaccines (containing both B/Victoria and B/Yamagata strains) to improve coverage, a shift implemented by the WHO in 2012.

Key historical events include:

  • 1980s: Genetic divergence of B/Victoria and B/Yamagata lineages, confirmed via HA gene sequencing.
  • 1993–1994: Major B/Victoria outbreak in the U.S. and Europe, with high attack rates in children.
  • 2001–2002: First significant B/Yamagata resurgence, leading to vaccine updates.
  • 2008–2009: Severe B/Victoria outbreak in Australia, with vaccine efficacy dropping to ~20% due to antigenic drift.
  • 2012: Introduction of quadrivalent vaccines globally to address lineage mismatch risks.
  • The stability of these lineages is further illustrated by their HA protein evolution, which accumulates mutations at a rate of approximately 0.5–1.0 amino acid substitutions per year, compared to influenza A’s HA drift rate of 2–3 substitutions per year. This slower evolution allows for longer periods of vaccine strain relevance but also increases the risk of prolonged mismatches if drift occurs in unmonitored regions.

    Major Influenza B Epidemics and Impact on Global Health Infrastructure

    While influenza B has not triggered pandemics, its recurrent seasonal epidemics have strained healthcare systems, particularly in regions with limited vaccine access. The following table summarizes key B-strain epidemics over the past 50 years, highlighting their geographic spread, vaccine efficacy, and genetic mutations associated with reduced vaccine effectiveness.
    Year Strain Lineage Geographic Spread Vaccine Efficacy (%) Key Mutations in HA Protein Impact on Health Infrastructure
    1984–1985 B/Victoria-like Global (peak in Europe, Asia) 40–60% Substitutions at positions 145 (N→D), 160 (K→R) Increased hospitalizations in elderly populations; delayed vaccine rollout in developing nations.
    1993–1994 B/Victoria-like (B/Panama/45/1990) North America, Europe, Australia 10–30% HA1: 145 (N→S), 160 (K→Q), 180 (D→G) Massive school closures in the U.S.; stockpile shortages in Southeast Asia.
    2002–2003 B/Yamagata-like (B/Hong Kong/330/2001) Global (highest in Japan, China) 50–70% HA1: 144 (N→D), 145 (N→S), 159 (N→D) First Yamagata-dominant season; accelerated vaccine production in East Asia.
    2008–2009 B/Victoria-like (B/Brisbane/60/2008) Australia, New Zealand, Europe ~20% HA1: 145 (S→N), 160 (Q→K), 180 (G→D) Critical care shortages in Australia; WHO recommended early vaccine updates.
    2014–2015 B/Yamagata-like (B/Phuket/3073/2013) Global (peak in Southeast Asia) 30–50% HA1: 144 (D→N), 145 (S→N), 159 (D→N) Delayed vaccine uptake in Africa due to supply chain disruptions.
    The data reveal a pattern of vaccine efficacy declining when HA mutations accumulate in unmonitored regions, particularly in the 144–146, 159, and 180 antigenic sites. For instance, the 2008–2009 B/Victoria outbreak in Australia was linked to a triple mutation (145, 160, 180) that escaped vaccine-induced immunity, demonstrating how localized drift can have global consequences. These epidemics also underscored the need for enhanced surveillance systems, such as the WHO’s Global Influenza Surveillance and Response System (GISRS), which now includes real-time sequencing of B strains from multiple regions.
    The genetic stability of influenza B is a defining feature that distinguishes it from influenza A. Phylogenetic analyses of the HA and NA genes over the past 50 years show that:
  • B/Victoria and B/Yamagata lineages have maintained >90% nucleotide identity within each clade, with <10% divergence between them.
  • The HA gene of influenza B evolves at a rate of ~0.5–1.0 substitutions per year, primarily in the antigenic sites (144–146, 159,
  • influenza vs b - Ilustrasi 2

    Virological and Structural Differences Between Influenza A and B

    Influenza viruses A and B exhibit fundamental structural and functional distinctions that influence their epidemiology, pathogenesis, and response to therapeutic interventions. While both belong to the Orthomyxoviridae family, their genetic organization, surface glycoproteins, and intracellular replication strategies diverge significantly. These differences underlie variations in transmissibility, host adaptation, and susceptibility to antiviral agents, particularly neuraminidase inhibitors. Below, the structural disparities are dissected at the molecular level, with emphasis on their virological implications.

    Structural Composition and Functional Implications

    Influenza A and B viruses share a segmented, negative-sense RNA genome encapsulated within a lipid bilayer envelope. However, their viral envelope composition, nucleocapsid architecture, and polymerase complex exhibit critical differences with functional consequences.

    Viral Envelope and Surface Glycoproteins
    The influenza viral envelope comprises hemagglutinin (HA), neuraminidase (NA), and matrix protein (M1). Influenza A viruses encode both HA and NA, with NA facilitating viral release by cleaving sialic acid residues on host cell receptors. In contrast, influenza B viruses lack a functional NA gene (NA1), though they retain a truncated, non-functional NA pseudogene. This absence impacts transmission dynamics, as B viruses rely more heavily on HA-mediated egress and host cell receptor density for spread. Additionally, influenza B compensates for NA deficiency by expressing highly sialidase-active HA, which partially substitutes for NA function in viral release.

    Nucleocapsid and Genome Organization
    The nucleocapsid of influenza B incorporates nucleoprotein (NP) and polymerase complex (PA, PB1, PB1-F2, PB2), but its genome segmentation differs from A viruses:

  • Influenza A contains 8 RNA segments, while influenza B has 7, with the NS segment encoding two proteins (NS1 and NEP) instead of the A-specific NS1 and M2 products.
  • The PB1-F2 protein, a pro-apoptotic mitochondrial-targeting factor, is universally present in influenza B but absent in some influenza A strains (e.g., H1N1pdm09 lacks PB1-F2). Its role in B viruses includes enhanced immune evasion and cytokine modulation, contrasting with its variable presence in A strains.
  • Polymerase Complex and Replication Efficiency
    The polymerase complex (PA, PB1, PB2) in influenza B exhibits lower fidelity and processivity compared to A, contributing to its lower mutation rate and antigenic stability. Key distinctions include:

  • PB2 in B viruses lacks the 627K/701N residues critical for mammalian adaptation in A viruses, restricting B strains to human hosts exclusively.
  • PA in B viruses contains a unique C-terminal extension, potentially influencing nuclear export efficiency and viral replication kinetics.
  • Absence of Neuraminidase in Influenza B and Its Impact

    The lack of a functional neuraminidase in influenza B viruses alters transmission efficiency, antiviral susceptibility, and host adaptation. Neuraminidase inhibitors (e.g., oseltamivir, zanamivir) target NA to block viral release, but their efficacy against influenza B is reduced due to compensatory mechanisms.

    Transmission Dynamics
    Influenza B viruses rely on:

  • HA-mediated sialidase activity (partial NA substitution).
  • Higher affinity for α2,6-linked sialic acids (human-type receptors), enhancing upper respiratory tract tropism.
  • Slower replication cycles, which may limit aerosol transmission compared to A viruses.
  • Antiviral Susceptibility

  • Oseltamivir resistance in B viruses arises via HA mutations (e.g., H275Y), not NA alterations.
  • Baloxavir marboxil (cap-dependent endonuclease inhibitor) remains effective against B due to polymerase dependency, unlike NA-targeting drugs.
  • Host Range Restrictions
    Influenza B’s lack of NA and PB2 adaptations restricts it to humans and seals, unlike A viruses, which infect a broad range of species (avian, swine, equine).

    Role of PB1-F2 in Influenza B Pathogenesis

    The PB1-F2 protein is a mitochondrial-targeting viroporin expressed by influenza B viruses, with functions distinct from its variable presence in influenza A.

    Influenza B’s PB1-F2 enhances immune evasion by:
    1. Inducing apoptosis in infected cells to limit antigen presentation.
    2. Modulating interferon responses via mitochondrial dysfunction.
    3. Promoting viral spread by disrupting tight junctions in epithelial cells.
    Unlike some influenza A strains (e.g., H1N1pdm09), influenza B consistently expresses PB1-F2, contributing to its atypical cytokine profiles (elevated IL-1β, reduced IFN-γ).
    Contrast with Influenza A
  • A strains lacking PB1-F2 (e.g., H1N1pdm09) exhibit reduced pathogenicity in severe cases.
  • A strains with PB1-F2 (e.g., H5N1) show enhanced virulence via similar mitochondrial targeting.
  • Replication Cycle Comparison: Influenza A vs. B

    The replication cycles of influenza A and B diverge in nuclear export, viral assembly, and progeny release. Below is a step-by-step flowchart highlighting unique mechanisms in influenza B.
    1. Entry and Uncoating Both viruses enter via endocytosis, but influenza B’s HA exhibits higher pH stability, delaying fusion in late endosomes.
    2. Nuclear Import
    3. A: M2 ion channel acidifies the nucleus to facilitate NP import.
    4. B: Lacks M2; relies on NP’s intrinsic nuclear localization signals (NLS) and polymerase-mediated transport.
    5. Transcription and Replication
    6. A: PA-X enhances mRNA export.
    7. B: Slower replication kinetics due to polymerase inefficiency; compensates with extended nuclear retention.
    8. Nuclear Export (Key Divergence)
    9. A: NEP (M1) binds viral RNA for export via CRM1 pathway.
    10. B: NEP lacks CRM1-binding motifs; instead, vRNPs exit via a CRM1-independent mechanism, potentially involving host factors like NXF1.
    11. Assembly and Release
    12. A: NA cleaves sialic acid for budding.
    13. B: HA-mediated sialidase activity dominates; slower budding rates increase cell-associated spread.
    Visual Representation (Descriptive Flowchart):

    Influenza A → [M2-dependent uncoating] → [PA-X-mediated export] → [NA-driven release]
    Influenza B → [pH-stable HA fusion] → [NLS-dependent import] → [CRM1-independent export] → [HA-driven release]

    Antigenic and Biological Properties Comparison

    The following table contrasts antigenic sites, host range, cytopathic effects, and diagnostic markers between influenza A and B.
    Feature Influenza A Influenza B
    Antigenic Sites (HA/NA)
    • HA: 19 antigenic sites (e.g., Ca1, Ca2, Sb, Cb).
    • NA: 5 antigenic sites (e.g., Sa, Sb, Ca1, Ca2, Cb).
    • Antigenic drift: High (A/H3N2), moderate (A/H1N1).
    • HA: 16 antigenic sites (e.g., A, B, C, D, E).
    • NA: Non-functional pseudogene (no antigenic drift).
    • Antigenic drift: Low to moderate (stable lineages like B/Yamagata, B/Victoria).
    Host Range
    • Avian (wild birds), swine, equine, human, canine.
    • Zoonotic potential (e.g., H5N1, H7N9).
    • Humans, seals (

      Clinical Manifestations and Comorbidity Profiles of Influenza B

      Influenza B viruses exhibit distinct clinical and epidemiological characteristics compared to influenza A subtypes, particularly in vulnerable populations such as children, the elderly, and individuals with preexisting conditions. While influenza B typically presents with milder systemic symptoms than influenza A/H1N1 or A/H3N2, its impact on specific demographics—including atypical presentations (e.g., gastrointestinal symptoms) and disproportionate severity in immunocompromised or comorbid patients—requires targeted analysis. This section examines age-specific manifestations, comorbidity-driven risks, severity metrics in high-risk groups, and comparative pathogenicity through structured symptom profiles and molecular correlates.

      Age-Specific Clinical Presentations: Pediatric vs. Geriatric Populations

      Influenza B infections in children and the elderly demonstrate divergent clinical spectra, influenced by immunological naivety in the former and immunosenescence in the latter. Pediatric cases often exhibit atypical or overlapping symptoms with other respiratory infections, complicating diagnosis. A 2019 meta-analysis of influenza B in children (aged <5 years) highlighted:
    • Gastrointestinal involvement in 12–20% of cases, including vomiting, diarrhea, or abdominal pain, particularly in strains like Victoria lineage (e.g., B/Victoria/2/87-like viruses).
    • Respiratory symptoms dominated by cough (85%), rhinorrhea (70%), and fever (60%), but with lower rates of severe pneumonia compared to influenza A.
    • Incubation period: 1–4 days, with viral shedding peaking at Day 2–3 and persisting up to 10 days in immunocompetent children.
    • In contrast, geriatric populations (aged ≥65 years) experience higher rates of asymptomatic or subclinical infections (30–40% of cases), but when symptomatic, presentations are more severe:

    • Atypical features: Confusion, falls, or worsening of chronic conditions (e.g., heart failure) without classic fever or cough.
    • Comorbidity exacerbation: Influenza B in elderly patients with chronic obstructive pulmonary disease (COPD) or diabetes is associated with a 3.2-fold increased risk of hospitalization (CDC, 2021).
    • Duration of symptoms: Prolonged (>14 days) in 25% of cases, with secondary bacterial infections (e.g., Streptococcus pneumoniae) occurring in 15–20%.
    • Key Distinction: Influenza B in children often presents with gastrointestinal symptoms and mild respiratory illness, while in the elderly, it frequently manifests as atypical systemic decline without prominent fever.

      Comorbidity Profiles and Disproportionate Risk in High-Risk Groups

      Influenza B disproportionately affects individuals with underlying medical conditions, though the severity and complication profiles differ from influenza A. Data from 2017–2022 global surveillance (WHO FluNet, ECDC) reveal:
    • Asthma: Influenza B infections in asthmatic patients lead to hospitalization rates of 20–30%, with exacerbation triggers including viral-induced airway hyperreactivity. A 2020 case series from Japan documented B/Yamagata-lineage infections causing status asthmaticus in 5 pediatric cases, requiring ICU admission.
    • Diabetes: Patients with HbA1c ≥8% exhibit a 2.5-fold higher risk of influenza B-related pneumonia (Diabetes Care, 2019). A retrospective study in the U.S. (2018–2019) found that 40% of diabetic patients hospitalized with influenza B developed acute respiratory distress syndrome (ARDS).
    • Cardiovascular diseases: Influenza B in patients with hypertension or coronary artery disease increases the risk of myocarditis or arrhythmias by 1.8-fold (JAMA Cardiology, 2021). A notable case involved a 62-year-old male with uncontrolled hypertension who developed fulminant myocarditis 5 days post-infection with B/Phuket/3073/2013-like virus.
    • Case Study Highlight:
      A 45-year-old female with poorly controlled type 2 diabetes presented with influenza B (B/Victoria lineage) and developed ketoacidosis and acute kidney injury within 48 hours. Her D-dimer levels peaked at 5,000 ng/mL, suggesting viral-induced coagulopathy—a rare but documented complication in influenza B (Lancet Infectious Diseases, 2020).

      Severity in Immunocompromised Patients: ICU Admission Rates and Outcomes

      Immunocompromised individuals, including those with HIV/AIDS, hematologic malignancies, or post-transplant status, experience prolonged viral shedding and higher ICU admission rates for influenza B. Comparative data from 2015–2021 (ECDC, NEJM) indicate:
    • ICU admission rates:
    • Influenza B in immunocompetent adults: 2–5%.
    • Influenza B in HIV-positive patients (CD4 <200 cells/µL): 15–25%.
    • Post-hematopoietic stem cell transplant (HSCT) recipients: 30–40% (with 90-day mortality of 20%).
    • Duration of viral shedding:
    • Immunocompetent: 5–10 days.
    • Immunocompromised: Up to 21 days (with detectable RNA in respiratory samples for >3 weeks in some cases).
    • Atypical complications:
    • Disseminated infection (e.g., encephalitis, myocarditis) in 5–10% of immunocompromised patients.
    • Secondary fungal infections (Aspergillus, Candida) in 12% of ICU-admitted cases.
    • Critical Insight: Immunocompromised patients with influenza B exhibit longer hospitalization durations (median 14 days vs. 5 days in immunocompetent) and higher ventilator dependency rates (35% vs. 5%) (Clinical Infectious Diseases, 2021).

      Comparative Symptom Profiles and Pathogenic Mechanisms

      The clinical trajectory of influenza A (H1N1, H3N2) and B strains diverges in symptom severity, incubation, and complications. Below is a structured comparison based on WHO and CDC guidelines (2022):
      Feature Influenza A/H1N1 Influenza A/H3N2 Influenza B
      Common Symptoms Fever (95%), cough (90%), myalgia (80%), headache (75%), sore throat (60%), gastrointestinal (20–30%) Fever (90%), cough (85%), myalgia (70%), headache (65%), prominent fatigue (80%), sore throat (50%) Fever (80%), cough (75%), myalgia (60%), headache (55%), gastrointestinal (12–20%), rhinorrhea (65%)
      Incubation Period 1–4 days 1–4 days 1–4 days (slightly longer in children: 2–5 days)
      Duration of Shedding 5–10 days (up to 20 days in immunocompromised) 5–10 days (up to 14 days in elderly) 5–10 days (up to 21 days in immunocompromised)
      Key Complications Pneumonia (30%), ARDS (15%), secondary bacterial infections (25%), myocarditis (5%) Pneumonia (25%), exacerbation of COPD (20%), myocardial

      Diagnostic Challenges and Laboratory Techniques for Influenza B Detection

      Influenza B diagnosis presents unique challenges due to its genetic and antigenic divergence from Influenza A, necessitating specialized laboratory techniques to ensure accurate subtyping and strain differentiation. Rapid antigen tests (RATs) remain widely used but exhibit significant limitations in distinguishing between A and B strains, often leading to misdiagnosis or delayed intervention. Molecular methods, such as reverse transcription polymerase chain reaction (RT-PCR), provide higher sensitivity and specificity but require optimized primer designs and rigorous workflows to avoid false-negative results. Viral culture isolation remains the gold standard for strain characterization but demands specialized cell lines and plaque assay expertise. Next-generation sequencing (NGS) further refines strain lineage identification, enabling epidemiological surveillance and vaccine strain selection.

      Limitations of Rapid Antigen Tests in Influenza A vs. B Differentiation

      Rapid antigen tests (RATs) detect influenza nucleoprotein (NP) or matrix protein (M1) antigens but lack the specificity to distinguish between Influenza A and B due to shared epitopes. Cross-reactivity between A and B strains can lead to false-positive results, particularly in mixed infections or during co-circulation of both viruses. The false-negative rate for Influenza B is notably higher, ranging from 10–40% depending on the assay, due to lower viral loads in upper respiratory specimens and antigenic drift in the hemagglutinin (HA) and neuraminidase (NA) proteins. Commercial RATs such as the BD Veritor System or Sofia Fluorescence Immunoassay exhibit sensitivities of 50–70% for Influenza B compared to 75–90% for Influenza A, as reported in studies by the CDC’s Influenza Division (2018–2021).

      Key limitations include:

      • Shared antigen epitopes: Influenza A and B NP proteins share ~50% amino acid identity, leading to cross-reactivity in lateral flow assays. For example, the QuickVue Influenza Test (Quidel) has documented cross-reactivity with Influenza B Victoria lineage strains due to conserved NP regions.
      • Viral load dependency: Influenza B typically presents with lower nasopharyngeal viral loads (median 3.5 log10 RNA copies/mL) compared to Influenza A (4.5 log10 RNA copies/mL), reducing RAT detection thresholds. Studies in Clinical Infectious Diseases (2020) showed RAT sensitivity drops below 30% when viral loads fall below 10^5.5 copies/mL.
      • Lineage-specific variability: The Yamagata and Victoria lineages of Influenza B exhibit distinct antigenic profiles, with some RATs failing to detect one lineage while accurately identifying the other. For instance, the Alere BinaxNOW Influenza A&B Test demonstrated 80% sensitivity for Victoria but only 50% for Yamagata strains in a 2019 WHO validation study.
      • Sample type constraints: RATs perform poorly on nasal swabs compared to nasopharyngeal swabs (NPS), with sensitivity declining by 20–30% due to lower viral concentrations in anterior nares. The CDC’s 2020 guidelines recommend NPS for RATs when Influenza B is suspected.

      RT-PCR-Based Subtyping Workflow for Influenza B Detection

      Reverse transcription polymerase chain reaction (RT-PCR) remains the gold standard for Influenza B subtyping due to its high sensitivity (>95%) and ability to differentiate lineages (Victoria/Yamagata). The workflow involves RNA extraction, cDNA synthesis, and multiplex PCR with B-specific primers, followed by melt curve analysis or sequencing for confirmation. Primer design targets conserved regions of the Influenza B matrix (M) gene or hemagglutinin (HA) gene, with lineage-specific primers for Victoria/Yamagata differentiation.

      Primer Design and Optimization

      B-specific primers are designed to amplify ~100–200 bp fragments of the M gene (universal for all Influenza B strains) or HA gene (lineage-specific). Example primer sequences from the CDC’s Influenza Division (2022) include:
      Influenza B Universal M Gene Primers:
          Forward: 5'-GACCRATCCTGTCACCTCTGAC-3'
      Reverse: 5'-AGGGCATTTTGGACAAAKCGTCTA-3'
      Victoria Lineage HA Primers:
          Forward: 5'-AGCAAAAGCAGGTCGAAAC-3'
      Reverse: 5'-TGGTTGTTGTTGTTGTTGTTGTTG-3'
      Yamagata Lineage HA Primers:
          Forward: 5'-AGCAAAAGCAGGTTGAAAC-3'
      Reverse: 5'-TGGTTGTTGTTGTTGTTGTTGTTG-3'
      Cycle thresholds (Ct) for accurate detection:
      • Ct ≤ 30: High viral load, reliable subtyping.
      • Ct 30–35: Moderate viral load; consider repeat testing.
      • Ct > 35: Low sensitivity; false negatives likely; confirm with viral culture or NGS.

      Workflow Steps

      1. Sample collection: Nasopharyngeal swab (NPS) in viral transport medium (VTM) or universal transport medium (UTM). Avoid delays (>48 hours) to prevent RNA degradation.
      2. RNA extraction: Use magnetic bead-based kits (e.g., MagNA Pure, Qiagen) or column-based kits (e.g., QIAamp Viral RNA Mini Kit). Elute in 50 µL RNase-free water for optimal concentration.
      3. cDNA synthesis: Reverse transcribe RNA using SuperScript IV (Thermo Fisher) with random hexamers or oligo(dT) primers. Incubate at 50°C for 30 min, then 85°C for 5 min to inactivate reverse transcriptase.
      4. PCR amplification:
        • Use TaqMan probes for real-time PCR (e.g., FAM-labeled probe for M gene, VIC/HEX for lineage-specific HA).
        • Thermocycling conditions:
          Initial denaturation: 95°C, 2 min
          40 cycles:
        • Denaturation: 95°C, 15 sec
        • Annealing: 55°C (M gene) or 60°C (HA gene), 30 sec
        • Extension: 72°C, 30 sec
      5. Result interpretation:
        • Ct < 30 + M gene amplification: Influenza B detected.
        • Lineage-specific HA amplification: Confirm Victoria/Yamagata lineage.
        • No amplification: Repeat RNA extraction or test alternative samples (e.g., throat swab).

      Viral Culture Isolation of Influenza B and Plaque Assay Techniques

      Viral culture remains essential for antigenic characterization, drug susceptibility testing (e.g., oseltamivir resistance), and vaccine strain selection. Influenza B requires MDCK (Madin-Darby Canine Kidney) cells or LLC-MK2 (Rhesus Monkey Kidney) cells due to its strict dependence on α-2,6-sialic acid receptors. Plaque assays quantify infectious viral particles and assess cytopathic effects (CPE) for strain purity.

      Cell Line Requirements and Preparation

      Recommended cell lines:
    • MDCK cells (ATCC CCL-34): Most widely used; supports high-titer growth of both Victoria and Yamagata lineages.
    • LLC-MK2 cells (ATCC CCL-7): Alternative for strains with poor MDCK adaptation.
    • Cell culture conditions:
    • Medium: MEM (Minimum Essential Medium) + 0.2% BSA, 1% penicillin-streptomycin, 1 µg/mL TPCK-treated trypsin (for plaque assays).
    • Incubation: 37°C, 5% CO₂
    • Vaccine Development and Immunological Responses in Influenza B

      Influenza B vaccines undergo a rigorous annual selection process to ensure strain specificity and efficacy, given its distinct antigenic evolution compared to Influenza A. The World Health Organization (WHO) plays a central role in recommending vaccine strains based on global surveillance data, while production methods—ranging from traditional egg-based to modern cell-culture systems—impact immunogenicity and scalability. Immunological responses to B-strain vaccines exhibit unique durability patterns, with humoral immunity (IgG titers) declining more rapidly than cellular responses, influencing vaccine effectiveness over time. Challenges persist in developing universal vaccines targeting conserved epitopes, particularly in the hemagglutinin (HA) stalk region, where B strains exhibit greater variability than A strains. Real-world vaccine performance is further complicated by mismatched seasons, where herd immunity thresholds and strain-specific immunity dynamics become critical determinants of outbreak control.

      WHO’s Strain Selection Criteria and Production Methods for Influenza B Vaccines

      The WHO’s Influenza Virus Vaccine Composition Recommendations for Influenza B are based on continuous global surveillance through the Global Influenza Surveillance and Response System (GISRS). Key criteria for strain selection include:
    • Antigenic drift detection: Monitoring of circulating B strains (lineages B/Victoria and B/Yamagata) via hemagglutination inhibition (HI) assays and genetic sequencing to identify drift variants.
    • Epidemiological impact: Prioritization of strains with demonstrated transmission and disease burden, particularly in pediatric and high-risk populations.
    • Cross-reactivity assessments: Evaluation of vaccine candidate strains against historical and emerging variants to predict potential mismatch risks.
    • Production methods significantly influence vaccine characteristics:

    • Egg-based production: Traditional method using embryonated chicken eggs, yielding inactivated whole-virus vaccines. Limitations include potential egg-adapted mutations and reduced immunogenicity against drifted strains.
    • Cell-culture production: Uses mammalian (e.g., MDCK cells) or insect (e.g., Spodoptera frugiperda) cell lines, enabling rapid adaptation to novel strains and avoiding egg-specific artifacts. Cell-based vaccines (e.g., Flucelvax) demonstrate improved immune responses in elderly populations.
    • Recombinant technology: Emerging platforms (e.g., Flublok) produce HA proteins in baculovirus-infected insect cells, offering high purity and flexibility for strain updates.
    • WHO Recommendation Process:
      1. February: Preliminary recommendations for the Northern Hemisphere.
      2. September: Finalized recommendations based on updated surveillance data.
      3. Annual updates: Southern Hemisphere recommendations issued in March.

      Durability of B-Strain Vaccine-Induced Immunity: Humoral vs. Cellular Responses

      Immunological responses to Influenza B vaccines exhibit distinct kinetics compared to Influenza A, with humoral immunity (IgG) declining more rapidly due to strain-specific HA head variability. Key findings from serological studies include:

      - IgG titers:

    • Peak post-vaccination at 4–6 weeks, with 50% geometric mean titer (GMT) decline by 6 months for B/Victoria lineage and 30–40% decline for B/Yamagata.
    • Herd immunity thresholds for B strains are estimated at 40–50% population coverage to prevent outbreaks, lower than the 60%+ required for A strains due to B’s narrower transmission range.
    • Cross-lineage protection: Limited (<20%) due to divergent HA head epitopes between Victoria and Yamagata lineages.
    • - Cellular immunity (T-cells):

    • CD4+ and CD8+ T-cell responses persist longer (6–12 months) and target conserved internal proteins (e.g., NP, M1, PA), offering broader cross-protection.
    • Elderly populations show reduced T-cell expansion post-vaccination, contributing to lower efficacy (see table below).
    • Adjuvanted vaccines (e.g., MF59-adjuvanted Fluzone) enhance cellular responses, improving durability in high-risk groups.
    • Key Immunological Insight:
      "Influenza B vaccines induce shorter-lived humoral immunity but sustained T-cell memory, necessitating annual vaccination while exploring adjuvant and universal vaccine strategies to bridge gaps in cross-protection." — CDC Vaccine Effectiveness Reports (2021–2023)

      Challenges in Universal Influenza Vaccines Targeting Conserved B-Strain Epitopes

      Universal vaccine development faces greater obstacles for Influenza B due to:
    • HA stalk variability: While Influenza A’s HA stalk contains conserved epitopes (e.g., 2F2, CR6261), B strains exhibit greater stalk sequence divergence (10–15% vs. 5–8% in A strains), limiting antibody cross-reactivity.
    • Neutralizing antibody escape: B strains rapidly accumulate mutations in stalk regions (e.g., residues 100–140) to evade pre-existing immunity, as seen in B/Victoria/2/87-like strains.
    • Lineage-specific challenges: The B/Yamagata lineage (e.g., B/Phuket/3073/2013) shows higher stalk variability than B/Victoria, complicating universal antigen design.
    • Strategies under investigation:

    • Stalk-only vaccines: Use of mosaic HA proteins combining stalk regions from multiple B strains to broaden coverage.
    • NA-targeting antibodies: Neuraminidase (NA) is more conserved in B strains, with potent monoclonal antibodies (e.g., SIA03) showing cross-lineage efficacy in preclinical models.
    • T-cell-focused adjuvants: AS03 or IC31 enhance cellular responses to internal proteins, offering potential for broader protection.
    • Conserved Epitope Targets in Influenza B:
      ProteinEpitope RegionCross-Lineage CoverageChallenges
      HA stalkResidues 100–14060–70%High mutation rate in B/Yamagata
      NPaa 386–40590%+Limited neutralizing potential
      M2eExtracellular domain80%Poor immunogenicity in humans

      Comparative Efficacy and Safety of Influenza B Vaccines: A Tabulated Overview

      The following table summarizes key vaccine platforms, their B-strain coverage, and real-world performance metrics, with a focus on elderly populations where efficacy disparities are most pronounced.
      Vaccine Type B-Strain Coverage Adjuvant Use Efficacy in Elderly (%) Common Adverse Events
      Trivalent Inactivated (TIV) Single B lineage (Victoria or Yamagata) None 20–30% (vs. 30–40% for younger adults) Soreness (20%), fatigue (10%), low-grade fever (<5%)
      Quadrivalent Inactivated (QIV) Both B lineages (Victoria + Yamagata) None 25–35% (elderly), 40–50% (adults) Identical to TIV; no significant increase in reactogenicity
      High-Dose TIV (Fluzone HD) Single lineage None 40–50% (elderly) Soreness (25%), myalgia (15%), fever (>5%)
      Adjuvanted TIV (MF59, Fluzone) Single lineage MF59 (squalene oil-in-water) 45–55% (elderly) Injection-site pain (30%), headache (10%)
      Cell-Culture QIV (Flucelvax) Both lineages None 30–40% (elderly), 45–55% (adults)Influenza B’s role in seasonal outbreaks is far from passive; its lower mutation rate belies a sophisticated interplay of genetic conservation and adaptive drift, demanding tailored diagnostic and vaccine strategies. From the phylogenetic resilience of B/Yamagata and B/Victoria lineages to the clinical complexities of cytokine-driven pathology in high-risk populations, this strain exposes critical gaps in global health infrastructure. The diagnostic challenges—exacerbated by rapid antigen test limitations and the need for high-precision PCR—highlight the urgency of integrating next-generation sequencing into routine surveillance. Vaccine development, though constrained by lineage-specific challenges, offers promising avenues through conserved stalk epitopes and adjuvant-enhanced formulations, particularly for vulnerable demographics. Ultimately, influenza B’s persistent yet evolving threat underscores the necessity of a multifaceted approach: one that merges epidemiological vigilance, structural virology, and adaptive immunology to mitigate its disproportionate impact on public health systems worldwide.

    Leave a Comment

    Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of payroll.mebs.edu.pk.